




Analysis of epidemiological characteristics and treatment of wounds in pediatric patients with hematologic malignancies
-
摘要:
目的 探讨血液系统恶性肿瘤患儿创面流行病学特点与治疗情况。 方法 该研究为回顾性病例系列研究。2017年1月—2024年12月,首都医科大学附属北京儿童医院收治20例、北京市顺义区妇幼保健院收治12例符合入选标准的血液系统恶性肿瘤患儿,共41个创面。统计患儿的性别、年龄、血液系统恶性肿瘤类型,创面成因、部位、出现时间、面积、深度、有无肿瘤侵及、合并感染、治疗方式、愈合时间、是否导致化学治疗延迟。根据创面深度,将其分为浅表创面组(30个)和深层创面组(11个),比较创面合并感染、有无肿瘤侵及、治疗方式、愈合时间及是否导致化学治疗延迟。根据创面有无肿瘤侵及,将其分为肿瘤创面组(11个)和普通创面组(30个),比较创面合并感染、深度、治疗方式、愈合时间及是否导致化学治疗延迟。根据创面治疗方式,将其分为手术治疗组(23个)和保守治疗组(18个),比较创面深度、有无肿瘤侵及、合并感染、愈合时间及是否导致化学治疗延迟。 结果 32例患儿男19例、女13例,年龄2.0~12.5岁,其中确诊为非霍奇金淋巴瘤者16例、急性髓系白血病者2例、急性淋巴细胞白血病者14例。6个创面为医源性创面,35个创面为非医源性创面。分别有9、9、11、12个创面累及头面颈部、躯干、四肢、臀部和会阴部。10个创面出现在肿瘤化学治疗之前,31个创面出现于肿瘤化学治疗过程中。创面面积为15.00(4.00,48.00)cm2。30个浅层创面、11个深层创面。11个创面有肿瘤侵及,31个创面合并感染。18个创面采取保守治疗,23个创面采取手术治疗。创面愈合时间为70.00(38.50,103.00)d。27个创面导致化学治疗延迟。浅表创面组和深层创面组创面合并感染情况、有无肿瘤侵及、治疗方式、愈合时间及是否导致化学治疗延迟比较,差异均无统计学意义(P>0.05)。肿瘤创面组创面愈合时间明显长于普通创面组(U=78.50,P<0.05)。手术治疗组创面合并感染、导致化学治疗延迟比例明显高于保守治疗组(P<0.05),创面愈合时间明显短于保守治疗组 ( U=112.00,P<0.05)。 结论 血液系统恶性肿瘤患儿的创面多为非医源性创面、多合并感染、愈合时间较长。创面的存在常导致肿瘤治疗延误,因此对有必要行手术治疗的创面早期识别和处理十分重要,手术治疗可加速创面愈合。 Abstract:Objective To explore the epidemiological characteristics and treatment of wounds in pediatric patients with hematologic malignancies. Methods This study was a retrospective case series study. From January 2017 to December 2024, 20 and 12 pediatric patients with hematologic malignancies meeting the inclusion criteria were admitted to Beijing Children's Hospital of Capital Medical University and Shunyi Maternal and Children's Hospital of Beijing Children's Hospital, respectively, yielding a total of 41 wounds. The following data were recorded, including gender, age, and type of hematologic malignancy of pediatric patients, wound etiology, location, time of onset, area, depth, presence of tumor invasion, concurrent infection, treatment modality, healing time, and whether the wound resulted in chemotherapy delay. According to the wound depth, the wounds were divided into superficial wound group (30 wounds) and deep wound group (11 wounds), and wound concurrent infection, presence of tumor invasion, treatment modality, healing time, and whether the wound resulted in chemotherapy delay were compared. According to the presence of tumor invasion, the wounds were divided into tumor-involved wound group (11 wounds) and ordinary wound group (30 wounds), and wound concurrent infection, depth, treatment modality, healing time, and whether the wound resulted in chemotherapy delay were compared. According to the treatment modality, the wounds were divided into surgical treatment group (23 wounds) and conservative treatment group (18 wounds), and wound depth, presence of tumor invasion, concurrent infection, healing time, and whether the wound resulted in chemotherapy delay were compared. Results Among the 32 pediatric patients, 19 were males and 13 were females, aged 2.0 to 12.5 years; 16 were diagnosed with non-Hodgkin lymphoma, 2 with acute myeloid leukemia, and 14 with acute lymphoblastic leukemia. Six wounds were iatrogenic and 35 wounds were non-iatrogenic. Nine, 9, 11, and 12 wounds involved the head, face and neck, trunk, extremities, and buttocks and perineum, respectively. Ten wounds appeared before chemotherapy, and 31 wounds appeared during chemotherapy. The wound area was 15.00 (4.00, 48.00) cm². Thirty wounds were superficial wounds, and 11 wounds were deep wounds. Eleven wounds showed tumor invasion, and 31 wounds had concurrent infection. Eighteen wounds received conservative treatment, and 23 wounds received surgical treatment. The wound healing time was 70.00 (38.50, 103.00) days. Twenty-seven wounds resulted in chemotherapy delay. There were no statistically significant differences between superficial wound group and deep wound group in concurrent wound infection, presence of tumor invasion, treatment modality, healing time, or whether the wound resulted in chemotherapy delay (P>0.05). The healing time of tumor-involved wound group was significantly longer than that in ordinary wound group (U=78.50, P<0.05). The percentages of concurrent infection and chemotherapy delay in surgical treatment group were significantly higher than that in conservative treatment group (P<0.05), with a significantly shorter healing time (U=112.00, P<0.05). Conclusions In pediatric patients with hematologic malignancies, wounds are mostly non-iatrogenic, with frequent concurrent infection and prolonged healing time. Because the presence of wounds frequently delays oncologic treatment, early identification and prompt treatment of wounds for which surgery is indicated are essential, and surgical treatment can accelerate wound healing. -
Key words:
- Child /
- Hematologic neoplasms /
- Wound Healing /
- Wound infection /
- Epidemiology /
- Immunosuppression
-
参考文献
(38) [1] 吴声,顾凯,庞怡,等.2002年至2021年上海市儿童青少年恶性肿瘤发病死亡特征及变化趋势分析[J].中华实用儿科临床杂志,2026,41(1):14-20.DOI: 10.3760/cma.j.cn101070-20250529-00395. [2] VoulgaridouA, AthanasiadouKI, AthanasiadouE, et al. Pulmonary infectious complications in children with hematologic malignancies and chemotherapy-induced neutropenia[J]. Diseases,2020,19,8(3):32.DOI: 10.3390/diseases8030032. [3] KaneE,KinseyS,BonaventureA,et al.Excess morbidity and mortality among survivors of childhood acute lymphoblastic leukaemia: 25 years of follow-up from the United Kingdom Childhood Cancer Study (UKCCS) population-based matched cohort[J].BMJ Open,2022,12(3):e056216.DOI: 10.1136/bmjopen-2021-056216. [4] XuY,ZhangA,LiuA,et al.Clinical analysis of immune reconstitution after chemotherapy in children with acute lymphoblastic leukemia[J].BMC Pediatr,2024,24(1):557.DOI: 10.1186/s12887-024-05030-4. [5] ChristopeitM,Schmidt-HieberM,SpruteR,et al.Prophylaxis, diagnosis and therapy of infections in patients undergoing high-dose chemotherapy and autologous haematopoietic stem cell transplantation. 2020 update of the recommendations of the Infectious Diseases Working Party (AGIHO) of the German Society of Hematology and Medical Oncology (DGHO)[J].Ann Hematol,2021,100(2):321-336.DOI: 10.1007/s00277-020-04297-8. [6] AksoyF,Karakoc ParlayanHN,AgirmanM,et al.Retrospective evaluation of the incidence, clinical characteristics and outcomes of Gram-negative bacterial infections in patients with hematologic malignancies[J].Pathogens,2025,14(12):1238.DOI: 10.3390/pathogens14121238. [7] LamaIY,CheungLK,JamesA,et al.Ecthyma gangrenosum: a case report in a child with acute lymphoblastic leukaemia[J].JPRAS Open,2024,40:215-221.DOI: 10.1016/j.jpra.2024.02.010. [8] PatilVL,ChavanDR,ThimmarayappaY,et al.Digital ischemia and gangrene: an unusual presentation of chronic myeloid leukemia[J].Cureus,2024,16(9):e70426.DOI: 10.7759/cureus.70426. [9] HouZ,MengD,RuanM,et al.A lesson from fatal invasive fungal infections after CAR-T cell therapy: a case report and literature review[J].Immunotherapy,2024,16(16/17):1021-1027.DOI: 10.1080/1750743X.2024.2404381. [10] KołodziejczykJ,CzarnyJ,KrólakS,et al.Successful treatment of Fournier's gangrene in child with relapsed acute lymphoblastic leukemia: case report and review of the literature[J].Infect Drug Resist,2025,18:1667-1673.DOI: 10.2147/IDR.S490240. [11] ParkJ,KimS,ShinSW,et al.Noma disease (cancrum oris, orofacial gangrene) in an acute myeloid leukemia patient: a case report[J].J Med Case Rep,2022,16(1):97.DOI: 10.1186/s13256-022-03317-7. [12] 孔祥力,石凯,张喜,等.Fournier坏疽临床诊断和综合治疗1例报告及文献复习[J].吉林大学学报(医学版),2024,50(4):1144-1149.DOI: 10.13481/j.1671-587X.202404030. [13] WangX,ZhangW,LuX,et al.Hematologic malignancies combined with acute necrotizing fasciitis: a report of 3 cases and literature review[J].Am J Transl Res,2026,18(1):626-636.DOI: 10.62347/TRWL2240. [14] ChengY,XueY,LiZ,et al.A nutrition-first, barrier-augmented, staged debridement management of grade IV oral mucositis in a leukemia patient with decompensated cirrhosis: a case report[J].Medicine (Baltimore),2026,105(21):e48943.DOI: 10.1097/MD.0000000000048943. [15] SiegelRL,KratzerTB,WagleNS,et al.Cancer statistics, 2026[J].CA Cancer J Clin,2026,76(1):e70043.DOI: 10.3322/caac.70043. [16] DaltveitDS, MorganE, ColombetM, et al. Global patterns of leukemia by subtype, age, and sex in 185 countries in 2022[J]. Leukemia,2025,39(2):412-419.DOI: 10.1038/s41375-024-02452-y. [17] WangP,CuiJ,NiZ,et al.A cross-sectional analysis of the global burden of childhood leukemia from 1990 to 2021[J].J Cancer Res Clin Oncol,2025,151(11):295.DOI: 10.1007/s00432-025-06247-1. [18] 王金容,王丽芬,林燕,等.以皮肤损害为首发症状的结外NK/T细胞淋巴瘤1例[J].临床皮肤科杂志,2021,50(11):686-687.DOI: 10.16761/j.cnki.1000-4963.2021.11.016. [19] Adithya SateeshB,BhagatYV,ThomasSE,et al.Recurrent bacterial infections in Cutaneous T-cell lymphoma[J].Cureus,2022,14(1):e20912.DOI: 10.7759/cureus.20912. [20] MunnangiV,JohnL,CunnigaiperN.Primary cutaneous diffuse large b-cell lymphoma presenting as a non-healing axillary ulcer[J].Cureus,2026,18(5):e108737.DOI: 10.7759/cureus.108737. [21] ChristensenBR,KouCJ,LeeLE.A rare case of extranodal natural killer/T-cell lymphoma, nasal type associated with hemophagocytic lymphohistiocytosis in a patient with recurrent sinusitis[J].Cureus,2024,16(3):e56237.DOI: 10.7759/cureus.56237. [22] TengX,WuJ,LiaoJ,et al.Advances in the use of ECMO in oncology patient[J].Cancer Med,2023,12(15):16243-16253.DOI: 10.1002/cam4.6288. [23] HaddadP,ChasinC,XuJ,et al.Single-center surgical site infection rate after peripheral ECMO decannulation and surgical repair[J].Ther Adv Infect Dis,2022,9:20499361221132148.DOI: 10.1177/20499361221132148. [24] SchmiegelowK,MüllerK,MogensenSS,et al.Non-infectious chemotherapy-associated acute toxicities during childhood acute lymphoblastic leukemia therapy[J].F1000Res,2017,6:444.DOI: 10.12688/f1000research.10768.1. [25] FogoA,duVivier A.The cutaneous manifestations of haematological malignancy[J].Clin Med (Lond),2009,9(4):366-370.DOI: 10.7861/clinmedicine.9-4-366. [26] PayneWG,NaiduDK,WheelerCK,et al.Wound healing in patients with cancer[J].Eplasty,2008,8:e9. [27] StaraceM,CarpaneseMA,PampaloniF,et al.Management of malignant cutaneous wounds in oncologic patients[J].Support Care Cancer,2022,30(9):7615-7623.DOI: 10.1007/s00520-022-07194-0. [28] 孙向东,李成志,悟拉木·艾力,等.股前外侧穿支皮瓣移植修复头面颈部皮肤恶性肿瘤根治性切除后创面的临床效果[J].中华烧伤与创面修复杂志,2025,41(1):28-35.DOI: 10.3760/cma.j.cn501225-20240920-00341. [29] 袁莹,周敏,漆白文,等.腹壁上动脉穿支筋膜皮瓣修复乳腺恶性肿瘤术后胸壁巨大创面的临床效果[J].中华烧伤与创面修复杂志,2025,41(9):895-901.DOI: 10.3760/cma.j.cn501225-20240930-00367. [30] 陈新冲,黄广涛.14例头面部瘢痕癌溃疡创面的临床诊疗分析[J].中国修复重建外科杂志,2024,38(3):342-347. DOI: 10.7507/1002-1892.202312020. [31] FurkaA, SimkóC, KostyálL, et al. Treatment algorithm for cancerous wounds: a systematic review[J]. Cancers (Basel),2022,14(5):1203.DOI: 10.3390/cancers14051203. [32] 李泽,张伟,杨飞,等.游离脐旁穿支皮瓣修复儿童皮肤软组织缺损创面的疗效研究[J].中国修复重建外科杂志,2025,39(5):633-638.DOI: 10.7507/1002-1892.202503130. [33] 杨焕纳,梁琰,韩大伟,等.人工真皮联合自体皮修复儿童手指电烧伤后骨骼和/或肌腱外露创面的效果[J].中华烧伤与创面修复杂志,2023,39(12):1180-1184.DOI: 10.3760/cma.j.cn501225-20231101-00168. [34] SłonimskaP,SachadynP,ZielińskiJ,et al.Chemotherapy-mediated complications of wound healing: an understudied side effect[J].Adv Wound Care (New Rochelle),2024,13(4):187-199.DOI: 10.1089/wound.2023.0097. [35] WuH,LiM,ShouC,et al.Pathogenic spectrum and drug resistance of bloodstream infection in patients with acute myeloid leukaemia: a single centre retrospective study[J].Front Cell Infect Microbiol,2024,14:1390053.DOI: 10.3389/fcimb.2024.1390053. [36] 任蓉,赵子年,张晴.儿童急性淋巴细胞白血病合并侵袭性真菌感染临床特点及疗效分析[J].中国病原生物学杂志,2025,20(1):81-85.DOI: 10.13350/j.cjpb.250115. [37] YasuT,SakuraiK,AkazawaM.Invasive fungal disease in patients with chronic lymphocytic leukemia in Japan: a retrospective database study[J].Curr Oncol,2022,29(5):3242-3251.DOI: 10.3390/curroncol29050264. [38] AlkanA,BuyukasikY,UzunO,et al.Invasive fungal infections in patients with acute leukemia: a retrospective cohort study at a tertiary-care hospital[J].Medicine (Baltimore),2024,103(40):e39959.DOI: 10.1097/MD.0000000000039959. -

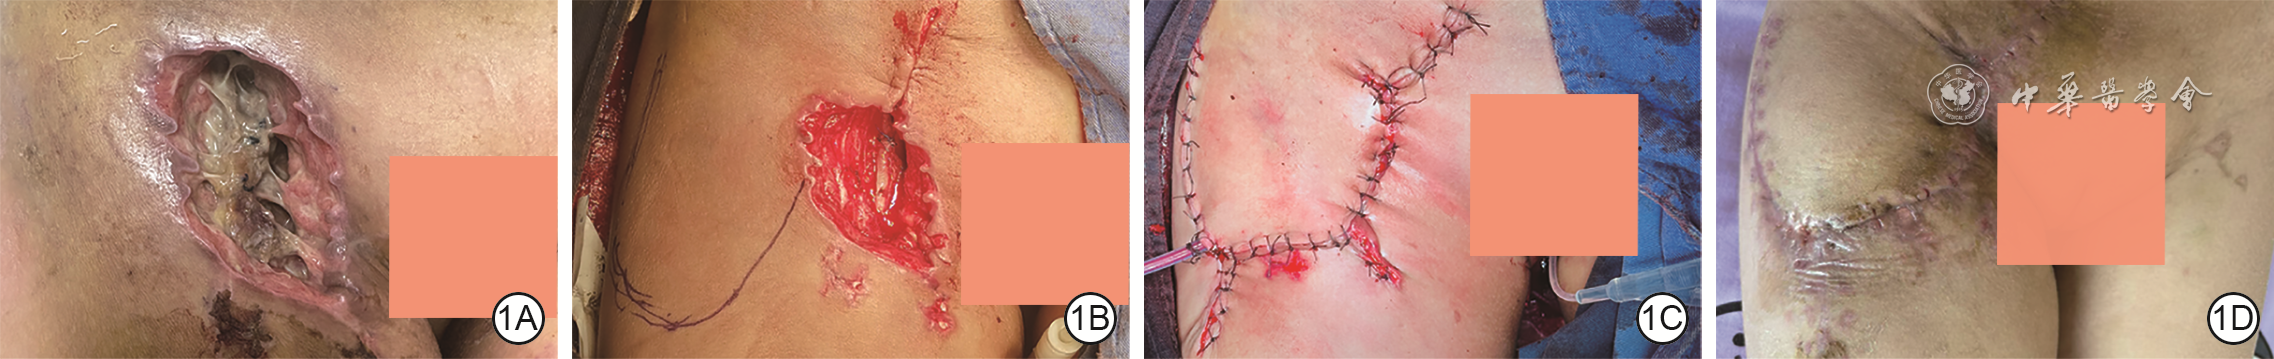
图 1 一例急性淋巴细胞白血病患儿右侧腹股沟创面的治疗效果。1A.右侧腹股沟创面出现第3天,创面深达肌层,较多坏死组织附着;1B.术中修补股动脉和彻底清创后;1C.转移局部皮瓣覆盖创面,缝合创面后;1D.术后37 d拆线后,创面完全愈合
Table 1. 不同血液系统恶性肿瘤患儿不同部位非医源性和医源性创面分布
血液系统恶性肿瘤类型 创面数(个) 头面颈部(个) 躯干(个) 四肢(个) 臀部和会阴部(个) 非医源性 医源性 非医源性 医源性 非医源性 医源性 非医源性 医源性 非医源性 医源性 非霍奇金淋巴瘤 16 5 6 0 3 4 2 1 5 0 急性淋巴细胞白血病 17 1 2 1 2 0 7 0 6 0 急性髓系白血病 2 0 0 0 0 0 1 0 1 0  下载: 导出CSV
Table 2. 浅表创面组和深层创面组血液系统恶性肿瘤患儿和创面基本资料比较
组别 患者例数 性别(例) 年龄(岁, 创面数(个) 创面部位(个) 创面面积[cm2,M(Q1,Q3)] 男 女 头面颈部 躯干 四肢 臀部和会阴部 浅表创面组 23 14 9 8.3±2.7 30 5 6 9 10 13.40(2.30,36.00) 深层创面组 9 5 4 6.8±2.8 11 4 3 2 2 15.60(4.00,100.00) 统计量值 — t=1.40 — U=109.50 P值 >0.999 0.173 0.465 0.265 注:根据创面深度是否达肌层,分为浅表创面组和深层创面组;“—”表示无此项
下载: 导出CSV
Table 3. 浅表创面组和深层创面组血液系统恶性肿瘤患儿创面特征比较
组别 创面数(个) 合并感染(个) 肿瘤侵及(个) 治疗方式(个) 愈合时间[d,M(Q1,Q3)] 导致化学治疗延迟(个) 有 无 有 无 手术治疗 保守治疗 是 否 浅表创面组 30 22 8 7 23 15 15 63.50(64.00,130.00) 17 13 深层创面组 11 9 2 4 7 8 3 85.00(36.00,94.00) 10 1 统计量值 — — — U=117.50 — P值 0.700 0.445 0.291 0.162 0.064 注:根据创面深度是否达肌层,分为浅表创面组和深层创面组;“—”表示无此项
下载: 导出CSV
Table 4. 肿瘤创面组及普通创面组血液系统恶性肿瘤患儿和创面基本资料比较
组别 患者例数 性别(例) 年龄(岁, 创面数(个) 部位(个) 创面面积[cm2,M(Q1,Q3)] 男 女 头面颈部 躯干 四肢 臀部和会阴部 普通创面组 25 14 11 8.2±2.7 30 6 6 8 10 13.50(3.58,36.00) 肿瘤创面组 7 5 2 6.9±2.8 11 3 3 3 2 15.00(4.00,100.00) 统计量值 — t=1.06 — U=128.00 P值 0.671 0.298 0.788 0.617 注:根据创面有无肿瘤侵及,分为肿瘤创面组和普通创面组;“—”表示无此项
下载: 导出CSV
Table 5. 肿瘤创面组及普通创面组血液系统恶性肿瘤患儿创面特征比较
组别 创面数(个) 合并感染(个) 深度(个) 治疗方式(个) 愈合时间[d,M(Q1,Q3)] 导致化学治疗延迟(个) 有 无 浅表创面 深层创面 手术治疗 保守治疗 是 否 普通创面组 30 21 9 23 7 17 13 63.50(37.50,86.00) 20 10 肿瘤创面组 11 10 1 7 4 6 5 168.00(64.00,240.00) 7 4 统计量值 — — — U=78.50 — P值 0.700 0.445 >0.999 0.011 >0.999 注:根据创面有无肿瘤侵及,分为肿瘤创面组和普通创面组;“—”表示无此项
下载: 导出CSV
Table 6. 手术治疗组与保守治疗组血液系统恶性肿瘤患儿和创面基本资料比较
组别 患者例数 性别(例) 年龄(岁, 创面数(个) 部位(个) 创面面积[cm2,M(Q1,Q3)] 男 女 头面颈部 躯干 四肢 臀部和会阴部 手术治疗组 19 10 9 8.1±2.9 23 4 6 6 7 12.00(4.00,36.00) 保守治疗组 13 9 4 7.6±2.8 18 5 3 5 5 18.00(4.25,60.00) 统计量值 — t=0.45 — U=192.00 P值 0.471 0.653 0.862 0.693 注:根据创面是否行手术治疗,分为手术治疗组和保守治疗组;“—”表示无此项
下载: 导出CSV
Table 7. 手术治疗组与保守治疗组血液系统恶性肿瘤患儿创面特征比较
组别 创面数(个) 合并感染(个) 深度(个) 肿瘤侵及(个) 愈合时间[d,M(Q1,Q3)] 导致化学治疗延迟(个) 有 无 浅表创面 深层创面 有 无 是 否 手术治疗组 23 21 2 15 8 6 17 42.00(36.00,97.00) 21 2 保守治疗组 18 10 8 15 3 5 13 86.00(64.25,159.00) 6 12 统计量值 — — — U=112.00 — P值 0.012 0.291 >0.999 0.013 <0.001 注:根据创面是否行手术治疗,分为手术治疗组和保守治疗组;“—”表示无此项
下载: 导出CSV
-

 下载:


计量
- 文章访问数: 1
- HTML全文浏览量: 1
- PDF下载量: 0
- 被引次数: 0
