





Clinical effect of multisegmental lymphatic-venous anastomosis in the treatment of post-traumatic lymphedema
-
摘要:
目的 探讨多节段淋巴管静脉吻合术(LVA)治疗创伤后淋巴水肿(PTL)的临床效果。 方法 该研究为回顾性病例系列研究。2024年1—8月,宁波市第二医院手显微修复外科收治7例符合入选标准的PTL患者,其中男3例、女4例,年龄51~75岁,病损累及上肢者3例、下肢者4例。患者均接受多节段LVA,即在肢体淋巴管受损部位以远,将真皮下脂肪浅层功能性集合淋巴管与附近瓣膜功能良好的浅表静脉吻合;在肢体淋巴管受损部位,将深筋膜浅层功能性集合淋巴管与附近瓣膜功能良好的浅表静脉吻合。术后均进行综合消肿治疗(CDT)。记录7例患者手术完成情况、并发症发生情况及PTL复发情况。比较3例上肢受累患者和3例下肢受累患者术前及术后3 d、1个月、3个月、6个月患侧肢体周径,使用人体成分分析仪测量的7例患者术前及术后14 d的体重、健侧与患侧肢体的肌肉均衡及生物电阻抗。 结果 7例患者均顺利完成手术。1例上肢受累患者患侧肢体于术后7 d发生淋巴管炎,经抗感染序贯CDT后,其肢体周径于术后1个月恢复至术后3 d水平;其余患者未发生手术相关并发症。7例患者术后随访期间PTL均未复发。术前及术后3 d、1个月、3个月、6个月,3例上肢受累患者患侧手与腕周径分别为(20.4±3.6)、(20.0±3.0)、(19.8±3.2)、(19.7±3.0)、(19.5±2.6)cm,前臂周径分别为(29±6)、(27±5)、(26±6)、(25±4)、(23±4)cm,上臂周径分别为(35±4)、(34±4)、(33±5)、(32±4)、(31±4)cm;3例下肢受累患者患侧足与踝周径分别为(27±4)、(25±4)、(25±5)、(24±4)、(24±4)cm,小腿周径分别为(38±9)、(35±8)、(34±8)、(33±8)、(33±8)cm,大腿周径分别为(49±10)、(47±10)、(47±10)、(46±10)、(46±10)cm。在患者患侧,术后3 d~术后6个月前臂、上臂、足与踝、小腿、大腿周径均较术前显著缩小(P<0.05),术后1~6个月前臂周径、术后3个月和6个月上臂周径、术后3个月足与踝周径、术后1~6个月小腿周径、术后3个月和6个月大腿周径均较术后3 d显著缩小(P<0.05),术后3个月与6个月前臂周径、术后3个月与6个月上臂周径、术后3个月足与踝周径、术后3个月和6个月大腿周径均较术后1个月显著缩小(P<0.05),术后6个月前臂和上臂周径均较术后3个月显著缩小(P<0.05)。与术前比较,7例患者术后14 d体重、患侧肢体肌肉均衡均显著下降(t值分别为3.181、3.221,P<0.05),患侧肢体生物电阻抗显著升高(t=-6.631,P<0.05)。 结论 在PTL外科治疗中,应用多节段LVA可缩小患侧肢体周径,有效改善水肿症状,联合CDT能持续增强疗效。 Abstract:Objective To investigate the clinical effect of multisegmental lymphatic-venous anastomosis (LVA) in the treatment of post-traumatic lymphedema (PTL). Methods This study was a retrospective case series study. From January to August 2024, 7 patients with PTL who met the inclusion criteria were admitted to the Department of Microprosthetic Hand Surgery of Ningbo NO.2 Hospital. There were 3 males and 4 females, aged 51-75 years. The lesions involved the upper limb in 3 patients and the lower limb in 4 patients. All patients underwent multisegmental LVA. Distal to the site of lymphatic injury in the limb, functional collecting lymphatic vessels in the superficial layer of the subdermal fat were anastomosed with adjacent superficial veins with good valvular function. At the site of lymphatic injury in the limb, functional collecting lymphatic vessels in the superficial layer of the deep fascia were anastomosed with adjacent superficial veins with good valvular function. After surgery, all patients received complete decongestive therapy (CDT). The completion of surgery, occurrence of complications, and recurrence of PTL were recorded for the 7 patients. The affected limb circumferences before surgery and at 3 days, 1 month, 3 months, and 6 months after surgery were compared among 3 patients with upper limb involvement and 3 patients with lower limb involvement. Body weight, muscle balance and bioelectrical impedance between the healthy and affected limbs measured by a body composition analyzer before surgery and at 14 days after surgery in 7 patients. Results All 7 patients completed the surgery successfully. One patient with upper limb involvement developed lymphangitis in the affected limb at 7 days after surgery. After anti-infective treatment followed by CDT, the limb circumference returned to the level at 3 days after surgery at 1 month after surgery. No adverse surgical complications occurred in the remaining patients. During postoperative follow-up, no recurrence of PTL was observed in the 7 patients. Before surgery and at 3 days, 1 month, 3 months, and 6 months after surgery, the hand and wrist circumferences at the affected side in the 3 patients with upper limb involvement were (20.4±3.6), (20.0±3.0), (19.8±3.2), (19.7±3.0), and (19.5±2.6) cm, respectively; the forearm circumferences were (29±6), (27±5), (26±6), (25±4), and (23±4) cm, respectively; the upper arm circumferences were (35±4), (34±4), (33±5), (32±4), and (31±4) cm, respectively; the foot and ankle circumferences at the affected side in the 3 patients with lower limb involvement were (27±4), (25±4), (25±5), (24±4), and (24±4) cm, respectively; the calf circumferences were (38±9), (35±8), (34±8), (33±8), and (33±8) cm, respectively; the thigh circumferences were (49±10), (47±10), (47±10), (46±10), and (46±10) cm, respectively. At the afftected side of patients, from 3 days to 6 months after surgery, the forearm, upper arm, foot and ankle, calf, and thigh circumferences were all significantly smaller than those before surgery (P<0.05), the forearm circumference at 1 to 6 months after surgery, the upper arm circumference at 3 and 6 months after surgery, the foot and ankle circumference at 3 months after surgery, the calf circumference at 1 to 6 months after surgery, and the thigh circumference at 3 and 6 months after surgery were all significantly smaller than those at 3 days after surgery (P<0.05), the forearm circumference at 3 and 6 months after surgery, the upper arm circumference at 3 and 6 months after surgery, the foot and ankle circumference at 3 months after surgery, and the thigh circumference at 3 and 6 months after surgery were all significantly smaller than those at 1 month after surgery (P<0.05), and the forearm and upper arm circumferences at 6 months after surgery were significantly smaller than those at 3 months after surgery (P<0.05). Compared with those before surgery, the body weight and muscle balance of the affected limb in the 7 patients at 14 days after surgery decreased significantly (with t values of 3.181 and 3.221, respectively, P<0.05), and the bioelectrical impedance of the affected limb increased significantly (t=-6.631, P<0.05). Conclusions In the surgical treatment of PTL, multisegmental LVA can reduce the affected limb circumference and effectively improve edema symptoms, and combined with CDT can continuously enhance the therapeutic effect. -
参考文献
(39) [1] UjiieN,KumeT.Mechanical forces in lymphatic vessel development: focus on transcriptional regulation[J].Front Physiol,2022,13:1066460.DOI: 10.3389/fphys.2022.1066460. [2] ManriqueOJ,BustosSS,CiudadP,et al.Overview of lymphedema for physicians and other clinicians: a review of fundamental concepts[J].Mayo Clin Proc,2022,97(10):1920-1935.DOI: 10.1016/j.mayocp.2020.01.006. [3] SudduthCL,GreeneAK.Primary lymphedema: update on genetic basis and management[J].Adv Wound Care (New Rochelle),2022,11(7):374-381.DOI: 10.1089/wound.2020.1338. [4] HossainL,GomesKP,SafarpourS,et al.The microenvironment of secondary lymphedema. The key to finding effective treatments?[J].Biochim Biophys Acta Mol Basis Dis,2025,1871(3):167677.DOI: 10.1016/j.bbadis.2025.167677. [5] DahlVA,TadisinaKK,HaleE,et al.Techniques and outcomes in microsurgical treatment of posttraumatic lymphedema: a systematic review[J].J Reconstr Microsurg,2024,40(8):635-641.DOI: 10.1055/a-2257-5345. [6] MinasianRA,SamahaY,BrazioPS. Post-traumatic lymphedema: review of the literature and surgical treatment options[J].Plast Aesthet Res,2022,9:18-27. [7] HircheC.Autologous breast reconstruction in conjuction with lymphatic microsurgery in breast cancer-related lymphedema[J].Handchir Mikrochir Plast Chir,2022,54(4):326-338.DOI: 10.1055/a-1868-5527. [8] LeeJW,LeeTY,MoonKC,et al.Lymphatic complex transfer as combined lymph vessel and node transfer for advanced stage upper extremity lymphedema[J].J Vasc Surg Venous Lymphat Disord,2023,11(4):824-831.e3.DOI: 10.1016/j.jvsv.2023.02.003. [9] MeroniM,MartiniF,ScaglioniMF.Systematic review of vascularized lymphatic vessel transfer for the treatment and prevention of lymphedema[J/OL].J Reconstr Microsurg,2026(2026-05-14)[2026-08-28].https://pubmed.ncbi.nlm.nih.gov/41730302/.DOI:10.1055/a-2817-4854.[published online ahead of print]. [10] 常鲲,夏松,孙宇光,等.联合应用抽吸减容术与淋巴静脉吻合术治疗下肢继发性淋巴水肿的临床效果[J].中华外科杂志,2017,55(4):274-278.DOI: 10.3760/cma.j.issn.0529-5815.2017.04.008. [11] KoshimaI,InagawaK,UrushibaraK,et al.Supermicrosurgical lymphaticovenular anastomosis for the treatment of lymphedema in the upper extremities[J].J Reconstr Microsurg,2000,16(6):437-442.DOI: 10.1055/s-2006-947150. [12] LinCH,YamamotoT.Supermicrosurgical lymphovenous anastomosis[J].J Chin Med Assoc,2024,87(5):455-462.DOI: 10.1097/JCMA.0000000000001088. [13] WangC,LiB,ZhongZ,et al. The"Overlapping"Lymphaticovenous Anastomosis: an overlapped end-to-end anastomosis supermicrosurgical technique[J].BMC Surg,2024,24(1):277.DOI: 10.1186/s12893-024-02568-z. [14] MarkarianB,ToroC,MoreiraK,et al.Assessment modalities for lower extremity edema, lymphedema, and lipedema: a scoping review[J].Cureus,2024,16(3):e55906.DOI: 10.7759/cureus.55906. [15] LiaoCD,KuruvillaAS,KrajewskiA.A scoping literature review of post-traumatic lymphedema: where are we now?[J].J Plast Reconstr Aesthet Surg,2022,75(7):2387-2440.DOI: 10.1016/j.bjps.2022.02.059. [16] DahlVA,TadisinaKK,XuKY. Limb salvage and treatment of posttraumatic lymphedema in a mangled lower extremity[J].Plast Reconstr Surg Glob Open,2024,12(10):e6209. DOI: 10.1097/GOX.0000000000006209. [17] PereiraN,OñateV,RoaR.A comprehensive approach to posttraumatic lymphedema surgical treatment[J].Arch Plast Surg,2023,50(4):422-431.DOI: 10.1055/s-0043-1768645. [18] 唐泽耀,邓呈亮.影像学技术在淋巴水肿诊疗中的应用进展[J/OL].中华损伤与修复杂志(电子版),2024,19(3):266-270.https://rs.yiigle.com/cmaid/1555464.DOI: 10.3877/cma.j.issn.1673-9450.2024.03.014. [19] van HeumenS,RiksenJ,BramerWM,et al.Imaging of the lymphatic vessels for surgical planning: a systematic review[J].Ann Surg Oncol,2023,30(1):462-479.DOI: 10.1245/s10434-022-12552-7. [20] OuC,LuoY,HeL,et al.Application of fluorescence endoscopy with methylene blue dye and indocyanine green dual-tracer method in sentinel lymph node biopsy for women with breast cancer [J].Gland Surg,2023,12(6):780-790.DOI: 10.21037/gs-22-469. [21] KamijoE,IshizukaK,ShikinoK,et al.Physical findings and tests useful for differentiating lymphedema[J].J Gen Fam Med,2021,22(4):227-228.DOI: 10.1002/jgf2.425. [22] KimMG,SonWC,KwonJG,et al.Clinical utility of bioimpedance analysis for upper limb lymphedema with surgical treatment[J].Lymphat Res Biol,2025,23(1):39-45.DOI: 10.1089/lrb.2022.0094. [23] SonWC,KwonJG,HongJP,et al.Clinical utility of bioelectrical impedance analysis parameters for evaluating patients with lower limb lymphedema after lymphovenous anastomosis[J].J Reconstr Microsurg,2023,39(3):171-178.DOI: 10.1055/s-0042-1750126. [24] YiL,JiangY,XuL,et al.Optimizing strategies for lymphaticovenular anastomosis in lower secondary extremity lymphedema[J].J Vasc Surg Venous Lymphat Disord,2025,13(1):101984.DOI: 10.1016/j.jvsv.2024.101984. [25] KwonJG,JeongS,PakCJ,et al.Comparative analysis between side-to-end and end-to-end lymphaticovenous anastomosis for secondary lower limb lymphedema[J].Plast Reconstr Surg,2022,150(5):1138-1148.DOI: 10.1097/PRS.0000000000009647. [26] ParkJW,KangJM,ChoiSY,et al.Comparison of the rate of concomitant proximal venous stenosis between the upper and lower extremities in patients with secondary lymphedema undergoing lymphaticovenous anastomosis[J].J Vasc Surg Venous Lymphat Disord,2025,13(1):101947.DOI: 10.1016/j.jvsv.2024.101947. [27] MotomiyaM,WatanabeN,OtaM,et al.A simple free flap strategy using end-to-side anastomosis to the main vessels in injured extremity[J].JPRAS Open,2023,38:48-59.DOI: 10.1016/j.jpra.2023.08.003. [28] LiuY,JiangY,ZhaoZ,et al.A functional deep cervical lymphovenous anastomosis model in APP/PS1 mice augmenting cerebral lymphatic drainage[J].J Neurosci Methods,2026,432:110779.DOI: 10.1016/j.jneumeth.2026.110779. [29] UnnoN,NishiyamaM,SuzukiM,et al.A novel method of measuring human lymphatic pumping using indocyanine green fluorescence lymphography[J].J Vasc Surg,2010,52(4):946-952.DOI: 10.1016/j.jvs.2010.04.067. [30] Ochsner JrA,Colp JrR,BurchGE. Normal blood pressure in the superficial venous system of man at rest in the supine position[J].Circulation,1951,3(5):674-680.DOI: 10.1161/01.cir.3.5.674. [31] ZhangW,LiJ,LiangJ,et al.Coagulation in lymphatic system[J].Front Cardiovasc Med,2021,8:762648.DOI: 10.3389/fcvm.2021.762648. [32] 唐泽耀,刘融,邓呈亮.超声技术在淋巴水肿诊断和治疗中的应用研究进展[J].中华烧伤与创面修复杂志,2026,42(3):297-302.DOI: 10.3760/cma.j.cn501225-20250228-00104. [33] Duygu-YildizE,BakarY,HizalM.The effect of complex decongestive physiotherapy applied with different compression pressures on skin and subcutaneous tissue thickness in individuals with breast cancer-related lymphedema: a double-blinded randomized comparison trial[J].Support Care Cancer,2023,31(7):383.DOI: 10.1007/s00520-023-07843-y. [34] ThompsonB,GaitatzisK,Janse de JongeX,et al.Manual lymphatic drainage treatment for lymphedema: a systematic review of the literature[J].J Cancer Surviv,2021,15(2):244-258.DOI: 10.1007/s11764-020-00928-1. [35] ZengY,LiuG,PengZ,et al.Application of complete decongestive therapy in patients with secondary bilateral lower limb lymphedema after comprehensive treatment of gynecological malignant tumor[J].Lymphat Res Biol,2024,22(1):60-65.DOI: 10.1089/lrb.2023.0029. [36] KimY,KimS,LimJY,et al.Home-based intermittent pneumatic compression therapy: the impact in chronic leg lymphedema in patients treated for gynecologic cancer[J].Healthcare (Basel),2022,10(4):638.DOI: 10.3390/healthcare10040638. [37] McKeownB,EhmannS,DavisS,et al.Categorising compression garments and accessories for upper-body lymphoedema[J].J Wound Care,2025,34(S11c):S30-S35.DOI: 10.12968/jowc.2025.34.S11c.S30. [38] SonWC,KimSA,KimAH,et al.Effects of forearm resistance exercises on breast cancer-related lymphedema using segmental bioelectrical impedance analysis: a pilot randomized controlled trial[J].J Clin Med,2024,13(23):7200.DOI: 10.3390/jcm13237200. [39] HaraH,MiharaM.Lymphaticovenous anastomosis reduces pain in selected patients with lower limb lymphedema[J].J Plast Reconstr Surg,2026,5(3):153-157.DOI: 10.53045/jprs.2025-0056. -

图 1 1例左侧上肢创伤后淋巴水肿患者采用多节段淋巴管静脉吻合术治疗前后大体情况及术前淋巴闪烁扫描检查情况。1A、1B、1C.分别为术前双上肢的掌侧面、桡侧面、背侧面,可见左侧上肢较右侧明显肿胀;1D、1E、1F.分别为术后3 d双上肢的掌侧面、桡侧面、背侧面,可见左侧上肢较右侧肿胀情况分别较图1A、1B、1C有所减轻;1G、1H、1I、1J.分别为术前正面淋巴闪烁扫描注射99mTc核素造影剂后10 min、1 h、3 h、6 h双上肢淋巴液的回流情况,可见左侧上肢淋巴回流受阻(几乎未见显影);1K、1L、1M、1N.分别为1G、1H、1I、1J对应背面淋巴闪烁扫描图

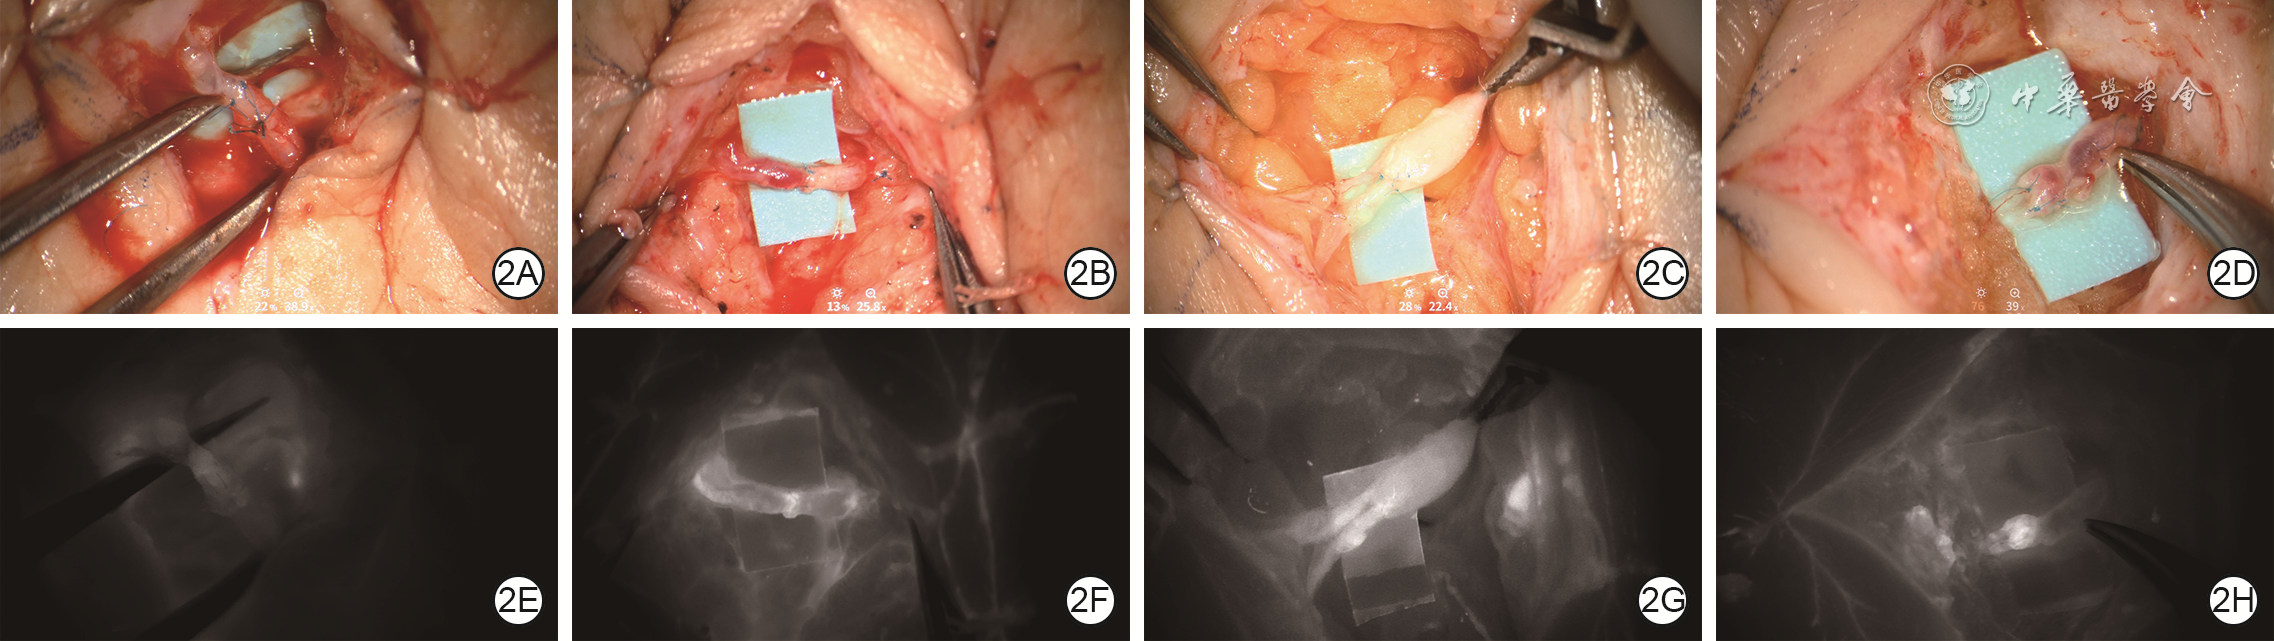
图 2 1例左侧上肢创伤后淋巴水肿患者行多节段淋巴管静脉吻合术中于荧光手术显微镜自然光与荧光模式下吻合情况。2A.自然光模式下于手背远端切口将1根淋巴管与静脉端端吻合后;2B.自然光模式下于手背近端切口将1根淋巴管与静脉端端吻合后;2C.自然光模式下于前臂切口将2根淋巴管套入静脉吻合后;2D.自然光模式下于上臂切口将2根淋巴管套入静脉吻合后;2E、2F、2G、2H.分别对应2A、2B、2C、2D荧光模式状态,可见淋巴液均顺利通过吻合口
Table 1. 7例创伤后淋巴水肿患者术前患侧与健侧肢体各部位周径比较(cm,
部位 样本数 患侧 健侧 t值 P值 手与腕 9 20.4±3.6 19.5±2.5 1.380 0.205 前臂 9 29±6 23±4 4.133 0.003 上臂 9 35±4 30±4 5.118 0.001 足与踝 12 26±4 24±4 4.121 0.002 小腿 12 37±9 32±7 3.814 0.003 大腿 9 49±10 45±10 2.921 0.019 注:上肢、下肢受累患者分别为3、4例,除1例患者因水肿局限于膝部及膝部以下仅测量足与踝、小腿2个部位的6个周径数据外,其余每例各测量3个部位共9个周径数据  下载: 导出CSV
Table 2. 6例创伤后淋巴水肿患者术前及术后各时间点患侧肢体各部位周径比较(cm,
部位 样本数 术前 术后3 d 术后1个月 术后3个月 术后6个月 时间效应F值 时间效应P值 手与腕 9 20.4±3.6 20.0±3.0 19.8±3.2 19.7±3.0 19.5±2.6 2.691 0.049 前臂 9 29±6 27±5a 26±6ab 25±4abc 23±4abcd 19.257 <0.001 上臂 9 35±4 34±4a 33±5a 32±4abc 31±4abcd 17.468 <0.001 足与踝 9 27±4 25±4a 25±5a 24±4abc 24±4a 11.762 <0.001 小腿 9 38±9 35±8a 34±8ab 33±8ab 33±8ab 15.550 <0.001 大腿 9 49±10 47±10a 47±10a 46±10abc 46±10abc 9.742 <0.001 注:上肢、下肢受累患者各3例,每例各测量3个部位共9个周径数据;时间效应F值、时间效应P值为每个部位各时间点总体比较所得;与术前比较,aP<0.05;与术后3 d比较,bP<0.05;与术后1个月比较,cP<0.05;与术后3个月比较,dP<0.05
下载: 导出CSV
Table 3. 创伤后淋巴水肿患者术前与术后14 d人体成分分析指标比较(
指标 例数 术前 术后14 d t3值 P3值 体重(kg) 7 64±11 62±10 3.181 0.019 患侧肢体肌肉均衡(kg) 7 9±5 7±4 3.221 0.018 健侧肢体肌肉均衡(kg) 7 6±4 6±4 0.476 0.651 患侧肢体生物电阻抗(Ω) 7 155±48 219±55 -6.631 0.001 健侧肢体生物电阻抗(Ω) 7 287±79 296±75 -0.907 0.399 t1值 4.075 3.501 P1值 0.007 0.013 t2值 -8.418 -6.068 P2值 <0.001 0.001 注:t1值、P1值为各时间点患侧与健侧肌肉均衡比较所得;t2值、P2值为各时间点患侧与健侧生物电阻抗比较所得;t3值、P3值为每个指标术前与术后14 d比较所得
下载: 导出CSV
-

 下载:



计量
- 文章访问数: 11
- HTML全文浏览量: 8
- PDF下载量: 1
- 被引次数: 0
