





Analysis of influencing factors for the occurrence of transient hypernatremia in patients with extensively severe burns
-
摘要:
目的 探讨特重度烧伤患者发生一过性高钠血症的影响因素。 方法 该研究为双向队列研究。回顾性分析空军军医大学第一附属医院2021年8月—2025年12月收治的126例符合入选标准的特重度烧伤患者(男97例、女29例,年龄18~64岁)的临床资料,统计高钠血症发生情况;在118例接受手术治疗的患者中,将于伤后≤5 d首次切痂的患者纳入早期切痂组(39例),将于伤后>5 d首次切痂的患者纳入晚期切痂组(79例),比较2组患者高钠血症发生率;根据是否使用悬浮床治疗,将患者分为悬浮床组(89例)与非悬浮床组(37例),比较2组患者高钠血症发生率,筛选特重度烧伤患者发生高钠血症的独立危险因素;针对于休克期行脉搏轮廓心输出量(PiCCO)监测患者,比较20例发生高钠血症患者与35例未发生高钠血症患者血管外肺水指数(EVLWI)和肺血管通透性指数(PVPI)。前瞻性纳入该院2025年5—12月收治的55例符合入选标准的特重度烧伤患者(男35例、女20例,年龄20~63岁),伤后3 d采集患者焦痂组织、创面皮肤组织、外周静脉血,采用随机数字表法选取5例发生高钠血症患者(设为高钠组)和5例未发生高钠血症患者(设为非高钠组)样本,采用电感耦合等离子体质谱法测定焦痂钠含量,采用酶联免疫吸附测定法检测血清中白细胞介素-1(IL-1)、IL-6、肿瘤坏死因子-α(TNF-α)及透明质酸水平,采用蛋白质印迹法检测创面皮肤组织中电压门控钠通道α亚基5(SCN5A)蛋白表达水平。 结果 在回顾性队列研究的126例患者中,50例(39.7%)患者伤后3~5 d发生高钠血症,其中41例患者高钠血症为一过性,9例患者死亡。41例发生一过性高钠血症患者血钠于伤后2~3 d开始上升,伤后5~8 d达峰值,至伤后10 d逐步恢复。晚期切痂组患者高钠血症发生率为32.9%(26/79),显著高于早期切痂组的7.7%(3/39),χ2=8.96,P<0.05。悬浮床组患者高钠血症发生率显著高于非悬浮床组(P<0.05)。多因素logistic回归分析结果显示,悬浮床治疗不是特重度烧伤患者发生高钠血症的独立危险因素(OR=1.80,95%CI为0.40~8.20,P>0.05),烧伤总面积与Ⅲ度烧伤面积均为特重度烧伤患者发生高钠血症的独立危险因素(OR分别为3.50、2.10,95%CI分别为1.90~6.70、1.20~3.80,P<0.05)。休克期行PiCCO监测患者中,发生高钠血症患者的EVLWI与PVPI均显著高于未发生高钠血症患者(t值分别为3.45、4.28,P<0.05)。在前瞻性队列研究中,高钠组患者伤后3 d焦痂钠含量为(128±9)mmol/kg,显著高于非高钠组的(102±6)mmol/kg(t=5.38,P<0.05)。与非高钠组比较,高钠组患者伤后3 d血清中IL-1、IL-6、TNF-α、透明质酸水平均显著升高(P<0.05),而创面皮肤组织中SCN5A蛋白表达水平显著降低(P<0.05)。 结论 特重度烧伤后一过性高钠血症并非单纯血钠升高,涉及焦痂钠蓄积、炎症介导的钠再分布及回吸收期钠释放。早期切痂可有效降低特重度烧伤患者发生一过性高钠血症的风险,其机制可能与移除部分含钠焦痂、减少钠释放有关。 Abstract:Objective To investigate the influencing factors for the occurrence of transient hypernatremia (TH) in patients with extensively severe burns. Methods This study was a bidirectional cohort study. Clinical data of 126 patients with extensively severe burns (97 males and 29 females, aged 18 to 64 years) who met the inclusion criteria and were admitted to the First Affiliated Hospital of Air Force Medical University from August 2021 to December 2025 were retrospectively analyzed. The incidence of hypernatremia was recorded. Among 118 patients who underwent surgical treatment, patients who underwent first escharectomy at ≤5 days after injury were included in early escharectomy group (n=39), and patients who underwent first escharectomy at >5 days after injury were included in late escharectomy group (n=79). The incidence of hypernatremia was compared between the two groups of patients. According to whether received air-fluidized bed (AFB) therapy, patients were divided into AFB group (n=89) and non-AFB group (n=37). The incidence of hypernatremia was compared between the two groups of patients, and independent risk factors for the occurrence of hypernatremia in patients with extensively severe burns were screened. For patients who underwent pulse contour cardiac output (PiCCO) monitoring during the shock stage, extravascular lung water index (EVLWI) and pulmonary vascular permeability index (PVPI) were compared between 20 patients with hypernatremia and 35 patients without hypernatremia. Fifty-five patients with extensively severe burns (35 males and 20 females, aged 20 to 63 years) who met the inclusion criteria and were admitted to this hospital from May to December 2025 were prospectively enrolled. At 3 days after injury, eschar tissue, wound skin tissue, and peripheral venous blood were collected. Using the random number table method, samples from 5 patients with hypernatremia (set as high Na+ group) and 5 patients without hypernatremia (set as non-high Na+ group) were selected. Sodium content in eschar was determined by inductively coupled plasma mass spectrometry. Serum levels of interleukin-1 (IL-1), IL-6, tumor necrosis factor-α (TNF-α), and hyaluronic acid were detected by enzyme-linked immunosorbent assay. Protein expression level of sodium voltage-gated channel alpha subunit 5 (SCN5A) in wound skin tissue was detected by Western blotting. Results In the retrospective cohort study of 126 patients, 50 patients (39.7%) developed hypernatremia 3 to 5 days after injury, among whom 41 patients had TH, and 9 patients died. In the 41 patients with TH, the serum sodium began to increase 2 to 3 days after injury, peaked 5 to 8 days after injury, and gradually recovered by 10 days after injury. The incidence of hypernatremia of patients in late escharectomy group was 32.9% (26/79), which was significantly higher than 7.7% (3/39) in early escharectomy group (χ2=8.96, P<0.05). The incidence of hypernatremia of patients in AFB group was significantly higher than that in non-AFB group (P<0.05). The results of multivariate logistic regression analysis showed that AFB therapy was not an independent risk factor for hypernatremia in patients with extensively severe burns (OR=1.80, with a 95% CI of 0.40 to 8.20, P>0.05), while both total burn area and full-thickness burn area were independent risk factors for hypernatremia in patients with extensively severe burns (with ORs of 3.50 and 2.10, respectively, 95% Cis of 1.90 to 6.70 and 1.20 to 3.80, respectively, P<0.05). Among patients who underwent PiCCO monitoring during the shock stage, EVLWI and PVPI in patients with hypernatremia were significantly higher than those in patients without hypernatremia (with t values of 3.45 and 4.28, respectively, P<0.05). In the prospective cohort study, sodium content in eschar at 3 days after injury in high Na+ group of patients was (128±9) mmol/kg, which was significantly higher than (102±6) mmol/kg in non-high Na+ group (t=5.38, P<0.05). Compared with those in non-high Na+ group, serum levels of IL-1, IL-6, TNF-α, and hyaluronic acid in high Na+ group of patients were significantly increased 3 days after injury (P<0.05), while the protein expression level of SCN5A in wound skin tissue was significantly decreased (P<0.05). Conclusions TH after extensively severe burns is not merely an elevation in serum sodium, but involves sodium accumulation in the eschar, inflammation-mediated sodium redistribution, and sodium release during the reabsorption phase. Early escharectomy can effectively reduce the risk of occurrence of TH in patients with extensively severe burns, and its mechanism may be associated with the removal of some sodium-containing eschar and a reduction in sodium release. -
Key words:
- Burns /
- Hypernatremia /
- Inflammation /
- Eschar accumulation /
- Release during the reabsorption phase /
- Early escharectomy /
- Transient
-
参考文献
(35) [1] MengerMM,WenzH,BambergM,et al.Severe burn injuries - the day the sodium starts rising[J].In Vivo,2024,38(2):747-753.DOI: 10.21873/invivo.13497. [2] SedghianiI,MoklineA,FredjH,et al.Hypernatremia risk factors and prognostic impact in burn patients: a case control study[J].Ann Burns Fire Disasters,2021,34(2):135-139. [3] RuggC,StröhleM,SchmidS,et al.The link between hypermetabolism and hypernatremia in severely burned patients[J].Nutrients,2020,12(3):774.DOI: 10.3390/nu12030774. [4] Van RegenmortelN,MoersL,LangerT,et al.Fluid-induced harm in the hospital: look beyond volume and start considering sodium. from physiology towards recommendations for daily practice in hospitalized adults[J].Ann Intensive Care,2021,11(1):79.DOI: 10.1186/s13613-021-00851-3. [5] Markl-Le LevéA,HillingerP,WoykeS,et al.The urea-creatinine ratio as marker of catabolism is affected by continuous renal replacement therapy[J].Diagnostics (Basel),2025,15(11):1408.DOI: 10.3390/diagnostics15111408. [6] StatlenderL,ShochatT,RobinsonE,et al.Urea to creatinine ratio as a predictor of persistent critical illness[J].J Crit Care,2024,83:154834.DOI: 10.1016/j.jcrc.2024.154834. [7] PaulusMC,MelchersM,van EsA,et al.The urea-to-creatinine ratio as an emerging biomarker in critical care: a scoping review and meta-analysis[J].Crit Care,2025,29(1):175.DOI: 10.1186/s13054-025-05396-6. [8] 沈嘉生,许永安.外泌汗腺汗液分泌离子通道调控机制研究进展[J].中华烧伤与创面修复杂志,2022,38(8):794-798.DOI: 10.3760/cma.j.cn501120-20210517-00191. [9] KanC,SkaggsJD.Current commonly used dynamic parameters and monitoring systems for perioperative goal-directed fluid therapy: a review[J].Yale J Biol Med,2023,96(1):107-123.DOI: 10.59249/JOAP6662. [10] VouloagkasI,AgbariahA,ZegkosT,et al.The many faces of SCN5A pathogenic variants: from channelopathy to cardiomyopathy[J].Heart Fail Rev,2025,30(1):247-256.DOI: 10.1007/s10741-024-10459-x. [11] 姜彬,都勇,夏一兰,等.特重度烧伤患者代谢高涨期进行基于间接测热法的营养治疗的效果[J].中华烧伤与创面修复杂志,2025,41(1):94-100.DOI: 10.3760/cma.j.cn501225-20240320-00103. [12] 高建川,柴家科,杨红明,等.早期切痂对重度烧伤患者静息能量消耗的影响[J].中华烧伤杂志,2004,20(1):37-39.DOI: 10.3760/cma.j.issn.1009-2587.2004.01.119. [13] Gwyn-JonesA,AfolabiT,BonneyS,et al.Major burns in adults: a practice review[J].Emerg Med J,2024,41(10):630-634.DOI: 10.1136/emermed-2024-214046. [14] RepellinM,CartonF,LolloG,et al.Alcian blue staining to visualize intracellular hyaluronic acid-based nanoparticles[J].Methods Mol Biol,2023,2566:313-320.DOI: 10.1007/978-1-0716-2675-7_25. [15] RajkumarJ,ChandanN,LioP,et al.The skin barrier and moisturization: function, disruption, and mechanisms of repair[J].Skin Pharmacol Physiol,2023,36(4):174-185.DOI: 10.1159/000534136. [16] KlotzT,IbrahimA,MaddernG,et al.Devices measuring transepidermal water loss: a systematic review of measurement properties[J].Skin Res Technol,2022,28(4):497-539.DOI: 10.1111/srt.13159. [17] NakanishiS,KamezonoR,NakataniM,et al.Comprehensive analysis of elemental distribution in human skin using laser ablation inductively coupled plasma mass spectrometry[J].Skin Res Technol,2021,27(4):576-581.DOI: 10.1111/srt.12986. [18] ArlatiS,AseniP.From evaporation to edema: a scoping review of physical and biological determinants of early fluid distribution in burn patients[J].Eur Burn J,2026,7(2):21.DOI: 10.3390/ebj7020021. [19] KlotzT,MoranH,VuP,et al.Commonly recommended moisturising products: effect on transepidermal water loss and hydration in a scar model[J].Burns,2025,51(8):107629.DOI: 10.1016/j.burns.2025.107629. [20] SivakumarAD,SharmaR,ThotaC,et al.WASP: wearable analytical skin probe for dynamic monitoring of transepidermal water loss[J].ACS Sens,2023,8(11):4407-4416.DOI: 10.1021/acssensors.3c01936. [21] ShinJ,SongJW,FlavinMT,et al.A non-contact wearable device for monitoring epidermal molecular flux[J].Nature,2025,640(8058):375-383.DOI: 10.1038/s41586-025-08825-2. [22] Olde EngberinkR,SelvarajahV,VogtL.Clinical impact of tissue sodium storage[J].Pediatr Nephrol,2020,35(8):1373-1380.DOI: 10.1007/s00467-019-04305-8. [23] MlejnekP,LiškaF,ŠilhavýJ,et al.Early reduction of skin potassium without sodium accumulation in the pathogenesis of salt sensitivity in primary aldosteronism[J].Front Pharmacol,2025,16:1575972.DOI: 10.3389/fphar.2025.1575972. [24] McIntoshM,CervantesH,OakesL,et al.Wound progression and healing in patients with deep tissue pressure injuries when placed on air-fluidized therapy versus low air loss support surface beds[J].J Wound Ostomy Continence Nurs,2025,52(4):279-284.DOI: 10.1097/WON.0000000000001196. [25] McNabbLJ,HyattJ.Effect of an air-fluidized bed on insensible water loss[J].Crit Care Med,1987,15(2):161-162.DOI: 10.1097/00003246-198702000-00017. [26] HellenthalK,BrabenecL,WagnerNM.Regulation and dysregulation of endothelial permeability during systemic inflammation[J].Cells,2022,11(12):1935.DOI: 10.3390/cells11121935. [27] YinB,JiangZ,ShiJ,et al.Hyaluronidase reverses the effect of hyaluronic acid without destroying normal skin structure[J].J Cosmet Dermatol,2026,25(5):e70870.DOI: 10.1111/jocd.70870. [28] SpasovskiG,VanholderR,AllolioB,et al.Clinical practice guideline on diagnosis and treatment of hyponatraemia[J].Intensive Care Med,2014,40(3):320-331.DOI: 10.1007/s00134-014-3210-2. [29] ZhangY,LiM,WangY,et al.Exosome/metformin-loaded self-healing conductive hydrogel rescues microvascular dysfunction and promotes chronic diabetic wound healing by inhibiting mitochondrial fission[J].Bioact Mater,2023,26:323-336.DOI: 10.1016/j.bioactmat.2023.01.020. [30] AbazariM,GhaffariA,RashidzadehH,et al.A systematic review on classification, identification, and healing process of burn wound healing[J].Int J Low Extrem Wounds,2022,21(1):18-30.DOI: 10.1177/1534734620924857. [31] ZhuZ,ZhouS,LiS,et al.Neutrophil extracellular traps in wound healing[J].Trends Pharmacol Sci,2024,45(11):1033-1045.DOI: 10.1016/j.tips.2024.09.007. [32] LuJ,ZhaoZ,PanL,et al.Hyaluronidase: structure, mechanism of action, diseases and therapeutic targets[J].Mol Biomed,2025,6(1):50.DOI: 10.1186/s43556-025-00299-y. [33] ZhangY,LiM,SongS,et al.Multiple dynamic crosslinked multifunctional hydrogels with glucose/pH dual-responsive adipose-derived stem cells-exosomes-releasing for diabetic wound healing[J/OL].Burns Trauma,2025,13:tkaf059[2025-12-19].https://pubmed.ncbi.nlm.nih.gov/41355885/.DOI: 10.1093/burnst/tkaf059. [34] ChenY,YinW,LiuZ,et al.Exosomes derived from fibroblasts enhance skin wound angiogenesis by regulating HIF-1α/VEGF/VEGFR pathway[J/OL].Burns Trauma,2025,13:tkae071[2025-12-19].https://pubmed.ncbi.nlm.nih.gov/40433567/.DOI: 10.1093/burnst/tkae071. [35] Yılmaz AydınF,AydınE,KadirogluAK.Comparison of the treatment efficacy of continuous renal replacement therapy and intermittent hemodialysis in patients with acute kidney injury admitted to the intensive care unit[J].Cureus,2022,14(1):e21707.DOI: 10.7759/cureus.21707. -

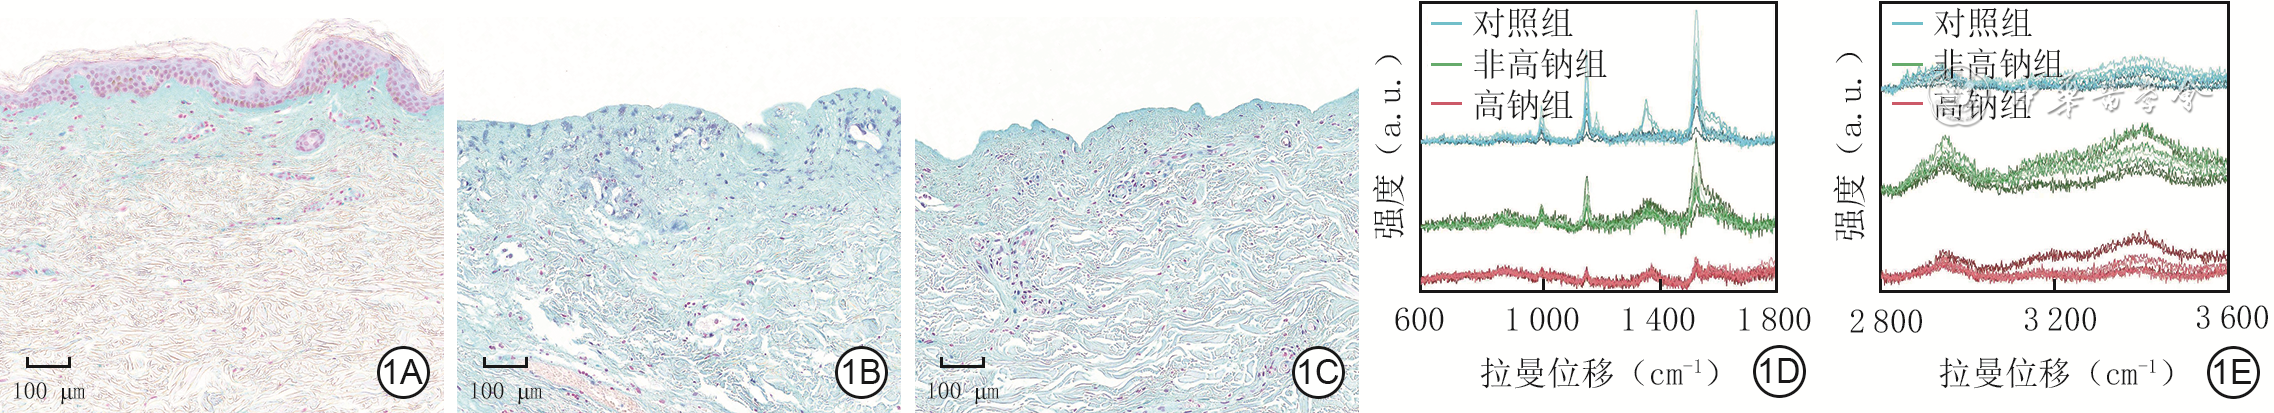
图 1 2组特重度烧伤患者伤后3 d创面皮肤组织与对照组腹壁整形患者正常皮肤组织中透明质酸分布及水与蛋白拉曼峰情况。1A、1B、1C.分别为对照组、非高钠组(患者未发生高钠血症)、高钠组(患者发生高钠血症)组织,图1B、1C中透明质酸(蓝色)呈弥漫性分布且明显多于图1A,图1C中透明质酸稍多于图1B 阿利新蓝 ×200;1D、1E.分别为蛋白/脂质指纹区、高波数水合区拉曼光谱分析图谱

图 2 2组特重度烧伤患者伤后3 d创面皮肤组织与对照组腹壁整形患者正常皮肤组织中炎症因子表达情况 二氨基联苯胺-苏木精 ×200。2A、2B、2C.分别为对照组IL-1、IL-6与TNF-α表达;2D、2E、2F.分别为非高钠组(患者未发生高钠血症)IL-1、IL-6与TNF-α表达,分别明显多于图2A、2B、2C;2G、2H、2I.分别为高钠组(患者发生高钠血症)IL-1、IL-6与TNF-α表达,分别明显多于图2D、2E、2F
注:白细胞介素1(IL-1)、IL-6、肿瘤坏死因子-α(TNF-α)阳性染色均呈棕色,细胞核阳性染色呈蓝色

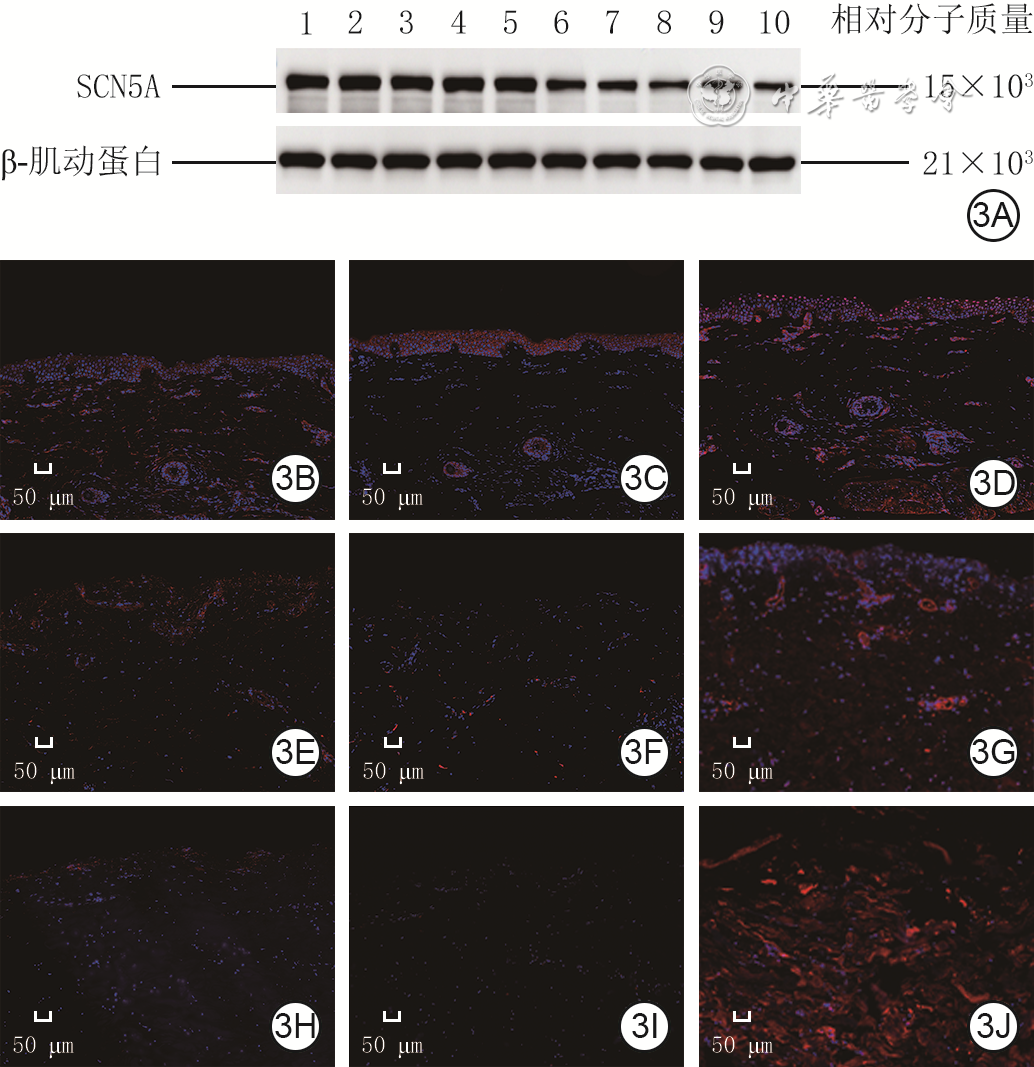
图 3 2组特重度烧伤患者伤后3 d创面皮肤组织与对照组腹壁整形患者正常皮肤组织中SCN5A、CD44、VE-cad及AngⅡ表达情况 Alexa Fluor 488-4′,6-二脒基-2-苯基吲哚 ×200 3A.蛋白质印迹法检测的SCN5A蛋白表达情况;3B、3C、3D.分别为对照组CD44、VE-cad及AngⅡ表达;3E、3F、3G.分别为非高钠组CD44、VE-cad及AngⅡ表达,图3E、3F中CD44、VE-cad表达分别明显少于图3B、3C,图3G中AngⅡ表达明显多于图3D;3H、3I、3J.分别为高钠组CD44、VE-cad及AngⅡ表达,图3H、3I中CD44、VE-cad表达分别明显少于图3E、3F,图3J中AngⅡ表达明显多于图3G
注:图3A中1~3、4~6、7~10分别指示对照组、非高钠组(患者未发生高钠血症)、高钠组(患者发生高钠血症)样本;SCN5A为电压门控钠通道α亚基5;CD44、血管内皮钙黏蛋白(VE-cad)及血管紧张素Ⅱ(AngⅡ)阳性染色均呈红色,细胞核阳性染色呈蓝色
Table 1. 早期切痂组和晚期切痂组特重度烧伤患者一般资料比较
组别 例数 性别(例) 年龄[岁,M(Q1,Q3)] 烧伤总面积(%TBSA, Ⅲ度烧伤面积[%TBSA,M(Q1,Q3)] 合并吸入性损伤(例) 男 女 早期切痂组 39 30 9 45.1(25.3,55.0) 72±8 60(57,65) 20 晚期切痂组 79 62 17 46.2(27.6,55.2) 75±6 62(59,66) 41 统计量值 χ2=0.04 Z=0.35 t=-2.28 Z=1.52 χ2<0.01 P值 0.848 0.537 0.024 0.137 0.950 注:早期切痂组患者于伤后≤5 d首次切痂,晚期切痂组患者于伤后>5 d首次切痂;TBSA为体表总面积  下载: 导出CSV
Table 2. 悬浮床组和非悬浮床组特重度烧伤患者一般资料比较
组别 例数 性别(例) 年龄[岁,M(Q1,Q3)] 烧伤总面积(%TBSA, Ⅲ度烧伤面积[%TBSA,M(Q1,Q3)] 合并吸入性损伤(例) 男 女 悬浮床组 89 70 19 47.1(23.1,56.0) 80±5 70(57,93) 43 非悬浮床组 37 27 10 46.7(25.4,56.7) 55±6 45(40,61) 18 统计量值 χ2=0.48 Z=0.25 t=24.07 Z=4.56 χ2<0.01 P值 0.490 0.732 <0.001 <0.001 0.973 注:悬浮床组患者使用悬浮床治疗,非悬浮床组患者未使用悬浮床治疗;TBSA为体表总面积
下载: 导出CSV
-

 下载:



计量
- 文章访问数: 3
- HTML全文浏览量: 3
- PDF下载量: 1
- 被引次数: 0
